

With only 1 day left, support Talking-up Scotland's work to counter the lies and get you the facts, daily, at:

Crowdfunder at: https://www.crowdfunder.co.uk/p/help-talking-up-scotland-keep-going

Or by direct bank transfer to: JOHN WATSON ROBERTSON Sort Code – 08-91-04 Account – 12266421
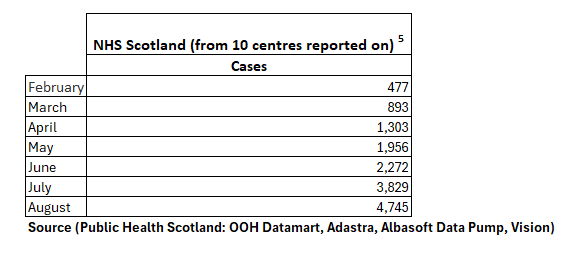
From GP led walk-in services monthly Month ending 31 August 2026 published today, the above table and this below:
- A case is used to identify a patient’s single encounter (service contact) with the Walk-In service.
- 2. Note that a patient can have more than one case at a centre in a month and will be counted on each occasion.
- 3. Clinics have been opened in a phased approach, so some have been open longer than others. Only the centre in NHS Lothian, Westerhailles Walk-in was open in February
- 4. Each clinic has different eligibility criteria and opening hours. Information on that can be found here.
- 5.Centes included : Centres are only included if they have a full month’s data for August. NHS Borders (Hawick), NHS Dumfries & Galloway (Stranraer), NHS Greater Glasgow and Clyde (Cardonald, Glasgow), NHS Grampian( Aberdeen city), NHS Highland (Dunoon, Invergordon), NHS Lothian (Wester Hailes) NHS Tayside (Lochee),NHS Shetland (Lerwick), and NHS Western Isles (Benbecula).
It remains too early to judge the success of these centres, as you. Why?
First, a reasonable science-based length for a pilot this kind to be meaningful would be at least 12 months and preferably 24 or 36 months after the initial ‘ramp-up period.’ We are still in the ramp-up period with only 10 of the 16 planned centres so far open. https://pmc.ncbi.nlm.nih.gov/articles/PMC10354383/
Second, learning from the English scheme has limits given the increasingly diverging NHS systems in England and Scotland but, in addition, it is important not to accept the BMA Scotland’s review of the evidence, selected only to back-up their prior views and, shamefully ignoring the work of Professor Chris Salisbury of the University of Bristol who gold-standard research revealed critical positive findings.
Improved access for certain groups: Centres clearly improved access, particularly for young and middle-aged men (historically lower users of traditional general practice) and people seeking care for recent-onset minor illnesses/injuries. Users often attended on the first day of symptoms for reasons of convenience, speed, and no need for an appointment.
High patient satisfaction: Users were generally more satisfied with walk-in centres than with general practice consultations (e.g., adjusted differences of around 6–7 percentage points in satisfaction scores). Care was viewed as high-quality and appropriate by both patients and staff in many assessments. Waiting times were often short and consultation times longer than typical GP appointments.
Safe, appropriate care for minor issues: Quality of care was at least comparable to general practice for the problems presented; most users felt the attendance was appropriate. https://www.bristol.ac.uk/media-library/sites/primaryhealthcare/migrated/documents/wiceval.pdf
Later patient surveys of GP-led walk-in centres similarly found high satisfaction (86–93% highly or fairly satisfied) and that centres increased access to GP-type care, with many attending because of difficulty seeing their own GP (working hours, closed surgery, or preference for no appointment). https://pmc.ncbi.nlm.nih.gov/articles/PMC3637583/
With only 1 day left, support Talking-up Scotland's work to counter the lies and get you the facts, daily, at:

Crowdfunder at: https://www.crowdfunder.co.uk/p/help-talking-up-scotland-keep-going

Or by direct bank transfer to: JOHN WATSON ROBERTSON Sort Code – 08-91-04 Account – 12266421
Discover more from Talking-up Scotland
Subscribe to get the latest posts sent to your email.


Between 1948 and 2004 GPs were contracted to work 24*7*365(6). The estimated cost of all GP out of hours work to the taxpayer – 128 hours per week – was 90p per hour which paid for all telephone answering (by unpaid GP partner or spouse), all medical care, all car costs and fuel, etc. https://abetternhs.net/2013/05/10/true-history/. The total amount was £6000 per full time GP per year and every NHS GP ran at a colossal loss. In cities GPs formed cooperatives, in towns small rotas and in isolated areas it was the full 24*7*365. A 56 hour shift on-call, sleep when you can was commonplace. NHS24 will cost ~£137million in running costs this year just to provide a contact service (not including the new software costing £48million to replace the last system loss of £117million). And now? GP services have poor availability and largely work on a ‘staff-centred’ not ‘patient-centred’ basis or maybe I’m the only one to experience rudeness and nonchalance. So, shut them all down and go back to walk-in and queue round the wall sixties style. Take a ticket for the queue management system with an approximation of your wait time. Cheap and effective. Let’s go back to a doctor and nurse system and forget all the pretendies. One of the few benefits of the 24*7*365(6) hours was experience and the development of a ‘sixth sense’ that something serious was amiss. All gone now. So keep and expand the walk-in centres (the GPs are milking the walk-in system anyway for doing what they should be doing in the first place!). “Oh…we’re so so busy”. Plenty of time for some to do private clinic work though, like some of their hospital colleagues. Those last two categories should GTF out of the NHS just like all the paramedical professionals they have inspired to do likewise.
LikeLike
Well said previous anonymous! Many private hospital systems operate as charities. And there is no VAT on private medical care. But for these oathbreakers (the doctors at least…“I solemnly pledge to dedicate my life to the service of humanity” and “The health and well-being of my patient will be my first consideration”…Hypocritical oath more like) their pockets are their first consideration. Even if the privateers actually work in their own time (how do they manage the unexpected events in their private hospitalised patients during NHS hours, just saying??) they are creating a two tier service and leaving the plebs with their ‘appointable’ but inexperienced junior staff. And dumping the occasional disasters back on the NHS. Destroying the private education system (VAT wouldn’t be allowed in EU, would it, SNP you hypocrites?) will actually cost Scotland huge sums of taxpayers money simply to have the system played by increased house prices in apartheid ‘good school areas’ instead. But the private healthcare system is indirectly subsidised by and depletes the NHS and not a whisper of loss of charitable status or VAT imposition. WTF is going on?
LikeLike